Few injuries are as frustrating as a rotator cuff problem. The shoulder — the most mobile joint in the body — becomes painful and limited, interfering with everything from getting dressed to sleeping to reaching overhead. And then comes the fear: “Do I need surgery?”
For the majority of rotator cuff injuries, the answer is no. Evidence-based physiotherapy has been shown to achieve outcomes equivalent to surgical repair for many partial and even some complete rotator cuff tears — without the risks, cost, and lengthy recovery of surgery.
At Rishaan Physio & Wellness Clinic in Mississauga, shoulder rehabilitation is one of our most commonly treated areas. Here is a comprehensive guide to rotator cuff injuries and how physiotherapy helps.
UNDERSTANDING THE ROTATOR CUFF
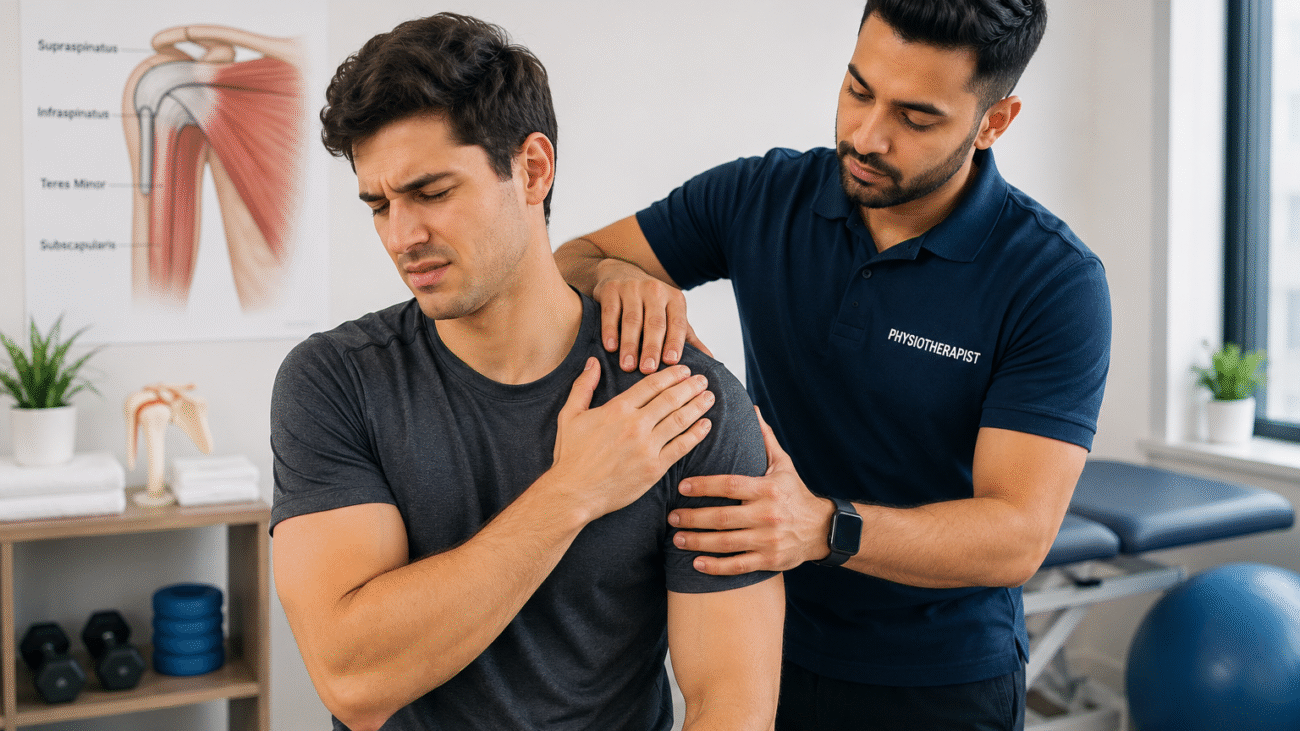
The rotator cuff is a group of four muscles and their tendons that surround the shoulder joint, holding the humeral head (the “ball”) in the glenoid fossa (the “socket”) and enabling shoulder rotation and elevation.
The four muscles are:
- Supraspinatus: Elevates the arm (most commonly injured)
- Infraspinatus: Externally rotates the shoulder
- Teres Minor: Also externally rotates
- Subscapularis: Internally rotates the shoulder
These muscles work together to provide dynamic stability during overhead and reaching activities. When one or more is injured, the entire shoulder mechanism is disrupted.
TYPES OF ROTATOR CUFF INJURIES
ROTATOR CUFF TENDINOPATHY (TENDINITIS)
The most common rotator cuff problem — gradual degeneration of the tendon fibres, usually from repetitive overhead activity, poor posture, or age-related changes. Symptoms include aching shoulder pain, especially with overhead movements, and nighttime pain. This responds very well to physiotherapy.
SUBACROMIAL IMPINGEMENT SYNDROME
The supraspinatus tendon or subacromial bursa becomes compressed (impinged) in the narrow space under the acromion bone when the arm is raised. Causes sharp pain with overhead activity and a painful arc of movement (typically between 60–120° of elevation).
PARTIAL THICKNESS TEAR
A tear that does not extend entirely through the tendon thickness. Partial tears can be managed very successfully with physiotherapy in most cases.
FULL THICKNESS TEAR (COMPLETE TEAR)
The tendon tears completely through its full thickness. Small to medium full-thickness tears often respond well to conservative physiotherapy. Large or massive tears involving multiple tendons are more likely to require surgical consideration.
ROTATOR CUFF CALCIFIC TENDINOPATHY
Calcium deposits form within the rotator cuff tendon (usually supraspinatus), causing episodic intense pain. Shockwave therapy has a very high success rate for this condition.
SYMPTOMS OF ROTATOR CUFF INJURY
- Shoulder pain with overhead movements (reaching, throwing, lifting)
- Nighttime shoulder pain (particularly lying on the affected side)
- Weakness in the shoulder — difficulty lifting objects, holding the arm elevated
- A painful arc of movement
- Clicking or catching sensation in the shoulder
– Gradual onset rather than sudden (in tendinopathy) or sudden onset with a specific incident (in acute tears)
HOW PHYSIOTHERAPY TREATS ROTATOR CUFF INJURIES
PHASE 1: PAIN RELIEF AND PROTECTION (Weeks 1–4)
- Manual therapy to restore joint mobility
- Soft tissue techniques for periscapular muscle tension
- Postural correction (forward shoulder posture is a key driver of impingement)
- Gentle pendulum exercises and range of motion
- Modalities: ice, ultrasound, TENS for pain management
- Activity modification guidance to protect the tendon during healing
PHASE 2: PROGRESSIVE STRENGTHENING (Weeks 4–12)
- Targeted rotator cuff strengthening — particularly external rotation and supraspinatus function
- Scapular stabiliser strengthening (serratus anterior, lower/middle trapezius)
- Proprioception and neuromuscular retraining
- Gradual return to functional activities
PHASE 3: FUNCTIONAL AND SPORT-SPECIFIC REHABILITATION (Weeks 8–16+)
- Sport or work-specific functional exercises
- Return to overhead activities, throwing sports, or heavy lifting (progressive loading)
- Eccentric strengthening protocols for tendinopathy
- Biomechanical correction of throwing, serving, or lifting mechanics
SHOCKWAVE THERAPY FOR ROTATOR CUFF CALCIFICATION
Extracorporeal shockwave therapy (ESWT) delivered by Rishaan Physio’s shockwave machine has demonstrated 70–80% success rates for calcific tendinopathy of the rotator cuff — often resolving calcium deposits and pain within 3–6 sessions without surgery.
IMS / DRY NEEDLING FOR PERSISTENT MUSCLE GUARDING
Chronic rotator cuff conditions often involve significant trigger point activity in the infraspinatus, supraspinatus, and periscapular muscles. IMS needle therapy at Rishaan Physio rapidly releases these trigger points, allowing more effective exercise rehabilitation.
CAN PHYSIOTHERAPY AVOID THE NEED FOR SURGERY?
For partial thickness tears: Yes — in the vast majority of cases, physiotherapy achieves complete pain relief and full functional recovery without surgery.
For full thickness tears: Research from the Journal of Bone and Joint Surgery (2021) found that 75% of patients with small to medium full thickness rotator cuff tears who received 12 weeks of structured physiotherapy reported equivalent outcomes to surgical repair at 2-year follow-up — without surgical risks, anaesthesia complications, or the 6–9 month post-surgical rehabilitation.
For large or massive tears: Surgery is more likely required, but prehabilitation before and physiotherapy after are still essential.
The current clinical guideline recommendation from most orthopaedic societies is a minimum 3-month trial of structured physiotherapy before surgical intervention is considered for rotator cuff injuries.
WHEN SURGERY IS NECESSARY
Consider surgical referral when:
- Physiotherapy has been consistently applied for 3–6 months without adequate improvement
- There is significant functional weakness that prevents essential activities
- Imaging shows a large or massive tear with fatty infiltration of the muscle (indicating muscle atrophy that cannot be rehabilitated)
- The patient is young and highly active with a specific demand requiring surgical repair
FREQUENTLY ASKED QUESTIONS
Q: How long does rotator cuff physiotherapy take?
A: Tendinopathy and partial tears: 6–12 weeks typically. Full thickness tears managed conservatively: 3–6 months. Post-surgical rotator cuff repair: 4–6 months.
Q: Can I exercise at the gym with a rotator cuff injury?
A: With guidance from your physiotherapist — yes, with modifications. Exercises to avoid include overhead pressing, lat pulldowns behind the neck, bench press with heavy loads, and throwing. Your physiotherapist will provide a modified gym program.
Q: Should I use ice or heat for rotator cuff pain?
A: Ice is preferred in the acute (first 48–72 hours after an injury or flare-up) phase. After the acute phase, heat can be used for general muscle relaxation before exercise. Neither is a long-term solution — physiotherapy addresses the cause, not just the symptoms.
Q: Will my rotator cuff tear get worse without surgery?
A: This is a nuanced question. Some tears remain stable with conservative management; some progress over time. Regular physiotherapy and monitoring with your physiotherapist and orthopaedic surgeon (if involved) is the appropriate approach.
Q: How do I book a shoulder assessment in Mississauga?
A: Contact Rishaan Physio directly at (905) 800-1661 or visit rishaanphysio.com. No referral is required.
BOOK YOUR SHOULDER ASSESSMENT IN MISSISSAUGA
Rishaan Physio & Wellness Clinic
5105 Hurontario St, Unit 7, Mississauga, ON
Phone: (905) 800-1661
Website: rishaanphysio.com
Open 7 days a week | Free pickup & drop-off available